
Estrogen is a family of hormones that supports reproductive function and also acts in the brain, bones, blood vessels, skin, and genitourinary tissues. During perimenopause, ovarian estrogen production becomes less predictable; after menopause, it is much lower and comes mainly from conversion of adrenal androgen precursors in peripheral tissues. These changes can contribute to hot flashes, vaginal and urinary symptoms, bone loss, and changes in sleep or cognition—but symptoms vary widely, and not every change in midlife is caused by estrogen.
This guide explains the main forms of estrogen, where they come from, how the menopause transition changes them, and what treatment options have evidence. It is educational information, not a diagnosis or personal treatment recommendation.

Key facts about estrogen and menopause
- Estradiol (E2) is the main, most potent estrogen during reproductive years; estrone (E1) is usually the predominant circulating estrogen after menopause, when total estrogen levels are much lower.
- Menopause is defined retrospectively after 12 months without a menstrual period. Perimenopause can involve substantial hormone fluctuation, not simply a smooth, gradual decline.
- Estrogen acts in multiple body systems, including bone, brain, blood vessels, skin, and vaginal and urinary tissues.
- Systemic menopausal hormone therapy is the most effective treatment for vasomotor symptoms such as hot flashes and night sweats, but suitability depends on an individual’s health history, goals, age, and timing.
- For someone with a uterus, systemic estrogen is generally paired with a progestogen to protect the uterine lining. Local low-dose vaginal estrogen is a different treatment with much lower systemic exposure.
- Hormone therapy is not a treatment for preventing cardiovascular disease or dementia. Treatment decisions require individualized discussion with a qualified clinician.
Estrogen is a family of hormones, not one substance
When people say “estrogen,” they often mean estradiol, but the term covers several related hormones. The three commonly discussed forms are:
- Estradiol (E2): the strongest of the main circulating estrogens and the predominant form during most reproductive years. The ovaries are its main source before menopause.
- Estrone (E1): less potent than estradiol at many estrogen receptors. It becomes the predominant circulating estrogen after menopause, although total estrogen levels are substantially lower than during reproductive years.
- Estriol (E3): a weaker estrogen that rises markedly during pregnancy. It is not the main hormone driving ordinary menopause symptoms.
These forms are not interchangeable in every context. Estrogen receptors are distributed across many tissues, and tissues can differ in which receptors they express, how they process hormones, and how they respond. So a single blood estrogen value cannot, by itself, describe how every body system is experiencing hormonal change.
Where estrogen comes from before and after menopause
Before menopause, the ovaries are the main source of estradiol. Production varies across the menstrual cycle and is coordinated with other reproductive hormones. During perimenopause, ovarian function becomes less regular: ovulation may not occur in every cycle, and hormone levels may swing from month to month. After menopause, ovarian estradiol production falls substantially.
The body does not make exactly zero estrogen after menopause. Adrenal glands produce androgen precursors—including DHEA and androstenedione. In peripheral tissues such as adipose (fat) tissue, enzymes convert these precursors into estrogens. Aromatase converts androstenedione to estrone and testosterone to estradiol; DHEA can feed into these pathways after additional conversion steps. This is a multi-step process, not DHEA turning directly into estrogen in one step. The accompanying diagram is a simplified pathway, not a complete map of steroid metabolism. [1, 2]
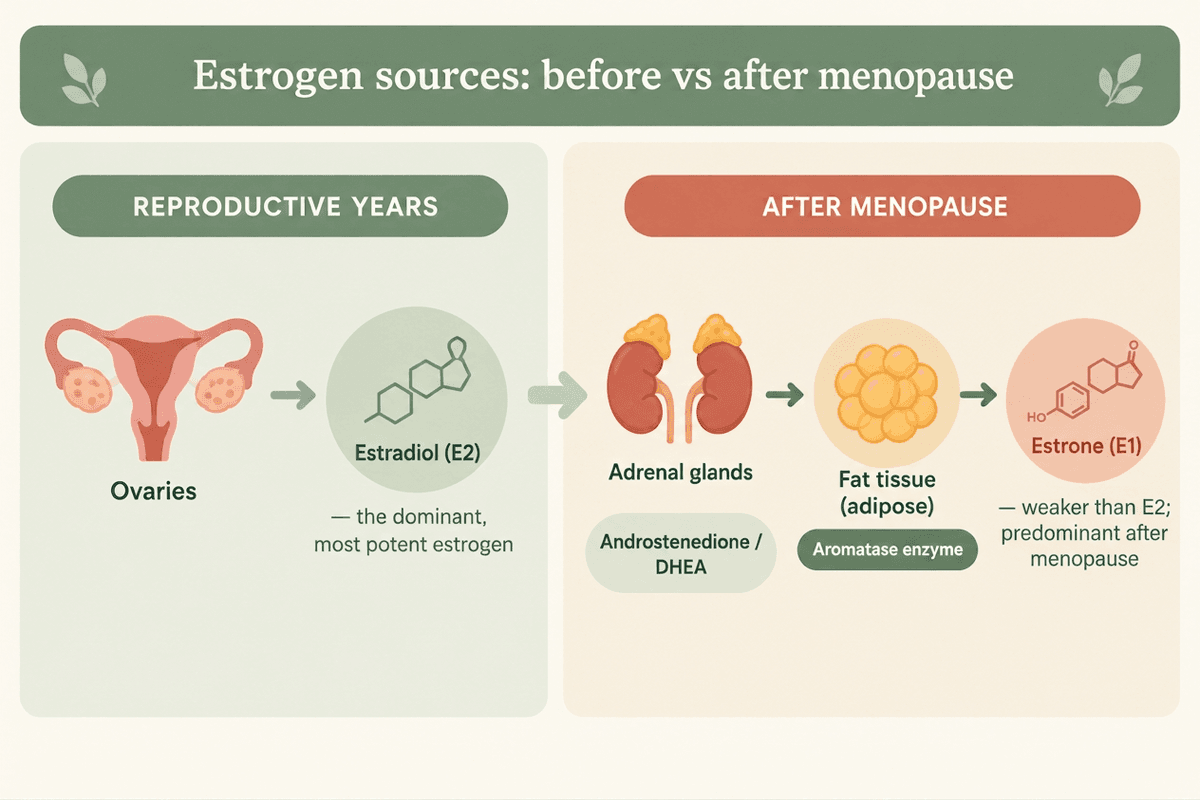
After menopause, estrone is generally the dominant circulating estrogen, while the overall estrogen environment is lower. The amount produced in peripheral tissue varies among individuals and is not something to try to “optimize” by changing body fat without medical guidance. Estrogen metabolism is influenced by age, genetics, body composition, medications, and health conditions; one diagram cannot predict a person’s hormone levels or cancer risk.
What estrogen does in the body
Estrogen is not only a reproductive hormone. It participates in many processes, but its effects are not identical in every person, and an association between estrogen and a body system does not prove that taking estrogen will prevent disease in that system.
Brain, mood, and cognition
Estrogen receptors are present in brain regions involved in mood, memory, attention, and temperature regulation. During the menopause transition, some people notice changes in sleep, mood, word-finding, or concentration. Those experiences are real, but they may also be affected by hot flashes, interrupted sleep, stress, medications, thyroid problems, depression, anemia, and other causes. Persistent, severe, or worsening cognitive symptoms should not automatically be attributed to menopause. [3, 4]
Research describes modest average changes in some cognitive measures during the transition; it does not mean that ordinary menopause-related brain fog is dementia or that estrogen therapy prevents dementia. If memory problems interfere with everyday life, a clinician can assess sleep, mood, medications, and other possible contributors.
Bones
Estrogen helps regulate bone remodeling. When estrogen levels fall, bone breakdown can outpace bone formation, and bone density may decline more quickly, especially around the early postmenopausal years. The effect varies with starting bone density, age, genetics, nutrition, activity, smoking, medications, and other health factors. Bone health is worth discussing as part of preventive care; a clinician can advise whether and when a bone-density scan is appropriate. [3, 5]
Systemic hormone therapy can prevent bone loss while it is being used and may be considered for eligible people with menopausal symptoms. It is not the only way to prevent or treat osteoporosis, and the choice depends on individual fracture risk and treatment goals.
Vaginal and urinary tissues
Lower estrogen can thin and dry vulvovaginal tissues and affect the lower urinary tract. Clinicians commonly call the persistent group of symptoms genitourinary syndrome of menopause (GSM). Symptoms can include dryness, irritation, pain with sex, urinary urgency, or recurrent urinary tract symptoms. Unlike hot flashes, GSM often persists or progresses without treatment. Other conditions can cause similar symptoms, so new pain, unusual discharge, or bleeding deserves assessment rather than self-diagnosis. [6]
Hot flashes and body temperature
Estrogen-sensitive neural pathways in the hypothalamus help regulate body temperature. During the menopause transition, changes in estrogen signaling can contribute to a narrower thermoneutral zone in some people. A small change in core temperature may then trigger heat-dissipation responses such as skin flushing and sweating. This is one important mechanism for vasomotor symptoms; it is not the only factor affecting whether someone experiences hot flashes or how severe they feel. [7]
Blood vessels, heart, and metabolism
Estrogen can influence blood-vessel function, cholesterol, and glucose metabolism. Menopause also occurs at an age when blood pressure, cholesterol, activity, sleep, and other cardiovascular risk factors may change. The rise in cardiovascular risk after menopause is not explained by estrogen alone. The available evidence does not support using systemic hormone therapy to prevent heart disease; assess and treat cardiovascular risk factors directly with a clinician. [3, 8]
Skin, hair, and connective tissue
Estrogen participates in collagen and skin physiology, so some people notice changes in skin dryness, elasticity, or hair during midlife. These changes are not specific to low estrogen: aging, thyroid conditions, iron deficiency, medications, skin disease, and other factors can contribute. Sudden or patchy hair loss, a painful or inflamed scalp, or persistent skin problems should be assessed rather than assumed to be hormonal.
Why the transition can feel like a roller coaster
Perimenopause is a transition, not an instant switch. Ovarian function can become irregular before periods stop, so estrogen levels may rise and fall. Symptoms can also vary over time and among people. Some have prominent hot flashes; others mainly notice sleep, mood, or cycle changes; some have few symptoms.
The final menstrual period can only be identified after 12 consecutive months without bleeding, when no other cause explains the absence of periods. The average age in the United States is about 51, but timing varies. Menopause before age 40 may indicate primary ovarian insufficiency (POI), which is medically distinct from typical-age menopause and merits clinical evaluation. [4, 9]
A single estradiol or FSH test usually cannot summarize a typical perimenopausal transition because values fluctuate. For most otherwise healthy people over 45 with characteristic cycle and symptom changes, clinicians can often identify perimenopause clinically; testing may be used in special circumstances or to check for another condition. ACOG advises that hormone testing is not generally useful as a routine way to decide whether to start menopause hormone therapy. [10]
What happens in a hot flash
A hot flash is a sudden sensation of heat that may affect the face, neck, or chest and can include flushing, sweating, or chills afterward. A leading biological model links estrogen withdrawal to changes in hypothalamic KNDy neurons—named for kisspeptin, neurokinin B, and dynorphin. These neurons participate in reproductive signaling and temperature regulation. When their activity changes, the range of temperatures the body tolerates without a heat-dissipation response may narrow. [7]
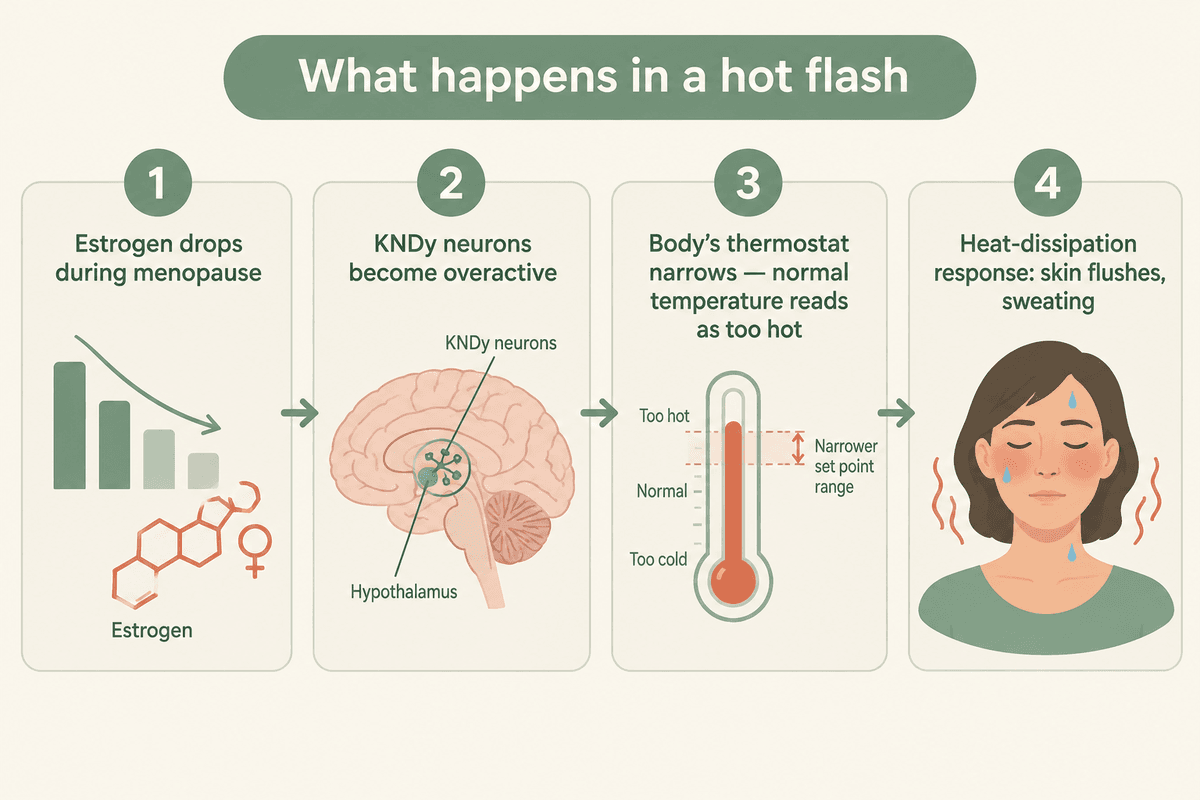
This model helps explain why treatments that affect estrogen signaling or the neurokinin pathway can reduce hot flashes. It does not mean every hot flash is caused by one isolated hormone level, and it does not let a reader diagnose the cause of new sweating. Fever, chest pain, fainting, or unexplained drenching sweats should be discussed promptly with a healthcare professional.
For related guides, see Hot Flashes, Night Sweats, and Insomnia.
How clinicians think about estrogen treatment
Treatment is based on the symptom being treated, medical history, treatment goals, and the person’s preferences—not on a target estrogen number alone. The options below are general information; they are not a personal recommendation.
Systemic menopausal hormone therapy
Systemic estrogen—taken as a pill, patch, gel, spray, or other formulation—is the most effective treatment for bothersome vasomotor symptoms. It can also prevent bone loss while used and may improve other symptoms for some people. Formulation, dose, route, and duration matter. The Menopause Society’s 2022 position statement and later guidance emphasize individualized assessment and periodic review; treatment is often considered for symptomatic people younger than 60 or within 10 years of menopause when there are no contraindications. [11]
If a person has a uterus, systemic estrogen is generally combined with a progestogen to protect the endometrium. Systemic estrogen alone is generally used after hysterectomy; personal history, including endometriosis, may change the discussion. Unopposed systemic estrogen in someone with a uterus can increase the risk of endometrial hyperplasia and cancer. [12]
The U.S. FDA approved updated labeling for six hormone-therapy products in February 2026, removing certain risk statements from those products’ boxed warnings. That is a change to product labeling—not a statement that hormone therapy has no risks, nor a blanket change to every product label or individual suitability. FDA advises patients and clinicians to consult the specific product label and make treatment decisions together. [13]
Systemic hormone therapy is not prescribed to prevent cardiovascular disease or dementia. For individuals with a history of breast cancer, blood clots, stroke, unexplained vaginal bleeding, significant liver disease, or other complex risks, treatment requires specialized individualized assessment; some options may not be suitable.
Local treatment for genitourinary symptoms
For vaginal and urinary symptoms, options may include lubricants, vaginal moisturizers, pelvic-floor treatment, and low-dose vaginal estrogen or other prescription therapies. Local low-dose vaginal estrogen is not the same as systemic estrogen: it is used to treat genitourinary symptoms and generally produces much lower systemic exposure. Whether it is appropriate depends on the symptoms, health history, and current medicines. New or postmenopausal bleeding always needs assessment.
Nonhormonal options for hot flashes
For people who cannot or prefer not to use systemic hormone therapy, options supported in The Menopause Society’s 2023 nonhormone statement include cognitive behavioral therapy (CBT), clinical hypnosis, selected SSRIs/SNRIs, gabapentin, fezolinetant, and in some cases oxybutynin. Weight loss has evidence for some people. Which options are appropriate depends on the person’s health, medicines, and preferences. [14]
Two neurokinin medicines are currently approved in the United States for moderate-to-severe vasomotor symptoms: fezolinetant (Veozah) and elinzanetant (Lynkuet). Their labels have distinct safety instructions. Fezolinetant carries an FDA boxed warning for rare but serious liver injury and requires liver testing before treatment and during treatment. Elinzanetant’s label calls for baseline liver tests and follow-up testing after three months, plus attention to drug interactions and other label warnings. These are prescription medicines; a clinician should review the current FDA label, possible interactions, and monitoring requirements. [15, 16]
Food, supplements, and everyday habits
A varied diet that supports bone, heart, and metabolic health can be worthwhile, but foods and supplements should not be presented as proven substitutes for effective treatment of hot flashes. Soy foods can be nutritious foods, but The Menopause Society’s 2023 evidence review does not recommend soy foods/extracts or herbal supplements as reliable treatments for vasomotor symptoms. The evidence for concentrated phytoestrogen products is mixed, and product quality and interactions vary. Ask a clinician or pharmacist before using a supplement, particularly alongside prescription medicines or a history of hormone-sensitive disease. [14, 17]
Cooling strategies, exercise, and avoiding a suspected personal trigger may help comfort or general health, but clinical evidence does not establish them as reliable standalone hot-flash treatments. Individual experiences differ. If a person notices a consistent trigger, keeping a symptom diary and discussing it with a clinician can help make decisions without assuming the trigger is universal.
The Hormone Connection
Estrogen interacts with other hormones and symptoms; it does not work alone:
- Progesterone helps regulate the uterine lining and changes across the cycle.
- Testosterone and DHEA are androgen-related hormones and precursors involved in peripheral estrogen production.
- Cortisol and thyroid hormones affect broader metabolism and can contribute to symptoms that overlap with menopause.
- Hot flashes, night sweats, brain fog, and vaginal dryness each have their own guides.
- Hormones Unveiled gives a broad overview; Your Adrenals covers adrenal androgen precursors.
Questions to bring to a healthcare professional
If symptoms are affecting daily life, consider noting when they occur, how they affect sleep or work, whether periods have changed, what medicines or supplements you take, and what you hope treatment will improve. Ask which options fit your personal medical history, whether local or systemic treatment is being discussed, what benefits to expect, what risks apply to your situation, and how follow-up will work. If a treatment is prescribed, ask how long to try it before reassessing and what symptoms should prompt contact.
When to seek medical care
Ask for a clinical evaluation if symptoms disrupt sleep or quality of life, if the cause is uncertain, or if symptoms persist despite treatment. Any bleeding after menopause—bleeding after 12 months without periods—requires prompt medical assessment. Severe or sudden chest pain, trouble breathing, fainting, or new neurological symptoms require urgent care and should not be attributed to menopause.
If menopause occurs before age 40, or periods stop unusually early, seek assessment for POI or another cause. People with persistent or worsening memory changes, severe depression or anxiety, new pelvic pain, or recurrent urinary symptoms should also discuss them with a healthcare professional.
Frequently asked questions
Does the body stop making estrogen after menopause?
Ovarian estradiol production falls substantially after menopause, but peripheral tissues continue making smaller amounts of estrogen from androgen precursors. Estrone is usually the predominant circulating estrogen after menopause. These lower hormone levels do not mean every person will have symptoms.
Can one blood test show whether I need estrogen?
Usually not during a typical perimenopausal transition: estrogen and FSH fluctuate, so a single reading may not represent the pattern. Clinicians generally consider symptoms, menstrual history, age, medical history, and goals. Testing can be useful in selected cases or to check for other conditions.
Is hormone therapy the same as birth control?
No. Menopausal hormone therapy and contraceptive pills have different formulations, doses, uses, and risk profiles. Pregnancy can still be possible during perimenopause. Ask a clinician about contraception and symptom treatment as separate questions.
Is hormone therapy safe for everyone?
No single treatment is right for everyone. Benefits and risks vary with the person’s age, time since menopause, health history, uterine status, formulation, route, dose, and goals. The FDA’s 2026 label changes for some products did not mean that hormone therapy is risk-free. Discuss current product labeling and your own situation with a clinician.
Do soy foods or supplements replace estrogen therapy?
No. Soy foods can be part of a balanced diet, but current evidence does not establish soy foods, isoflavone supplements, or herbal products as equivalent to prescription hormone therapy for hot flashes. Some products may interact with medicines or be unsuitable for some health histories.
References
- Estrogen deficiency in the menopause and the role of hormone therapy: integrating basic science with clinical trials, 2025 review.
- Metabolic impact of endogenously produced estrogens by adipose tissue across the lifespan, Frontiers in Endocrinology, 2025.
- How menopause affects heart, brain and bone health, Mayo Clinic, 2026.
- Menopause: symptoms, causes, diagnosis and treatment, Mayo Clinic.
- Menopause and bone loss, Endocrine Society.
- Genitourinary syndrome of menopause: an overview of the recent data, 2020 review.
- Modulation of body temperature and LH secretion by hypothalamic KNDy neurons: a novel hypothesis on the mechanism of hot flushes, Rance et al., 2013.
- The 2022 hormone therapy position statement of The North American Menopause Society, 2022.
- European Society of Endocrinology clinical practice guideline for evaluation and management of menopause and perimenopause, 2025.
- Should I have hormone testing before starting hormone therapy?, ACOG, 2025.
- The Menopause Society: FDA-approved hormone therapy labeling changes, FDA, February 12, 2026; and The Menopause Society’s response, November 2025.
- Hormone therapy and endometrial hyperplasia/cancer, systematic review, 2025; see also ACOG: Hormone Therapy for Menopause.
- The 2023 nonhormone therapy position statement of The North American Menopause Society, 2023.
- FDA Drug Trials Snapshot: Lynkuet (elinzanetant), approval October 24, 2025; see the FDA prescribing information.
- FDA safety communication: Veozah (fezolinetant) and rare serious liver injury, updated December 16, 2024.
- Efficacy of phytoestrogens for menopausal symptoms: systematic review and meta-analysis, 2015.
Disclaimer: This page is for general education and does not replace individual medical advice, diagnosis, or treatment. Options, approvals, and labels vary by country. Discuss symptoms, medicines, and treatment decisions with a qualified healthcare professional.